Council on Energy, Environment and Water Integrated | International | Independent


Suggested citation: Global Heat Health Information Network South Asia Hub. 2026. Living with Heat in India: Heat-Health Risks, Vulnerability and Emerging Responses

Please access Bangladesh, Nepal and Bhutan reports:
This report examines India’s evolving heat risk and its implications for population health, with a focus on changing heat exposure, the populations and places most at risk, and the institutional and policy responses emerging across the country. It assesses India’s progress in responding to extreme heat, identifies gaps in implementation, coordination, data and financing, and consolidates priorities for strengthening long-term heat resilience. The report also highlights practical approaches being tested on the ground and considers how emerging evidence can inform scalable, context-specific responses to the health, livelihood and socioeconomic impacts of extreme heat.
The report draws on historical and projected temperature data, alongside evidence on heat-related health impacts, vulnerability and adaptation. It examines India’s heat governance landscape, including Heat Action Plans (HAPs), health-system preparedness, heat-health surveillance, early warning systems, and interventions led by non-governmental and community-based organisations. It then identifies priorities for institutionalising long-term heat resilience, including mainstreaming heat action across sectors and levels of governance, strengthening institutional and health-system capacities and coordination, unlocking finance for adaptation, and embedding health outcomes in the planning, implementation and evaluation of heat action.

Extreme heat is a public health threat multiplier.
Increased frequency, intensity, and duration of extreme heat events have emerged as a climate, health, and development challenge, affecting the overall well-being of communities. Rising global temperatures drive the hazard; rapid unplanned urbanisation and entrenched inequality determine who it harms. The warming record is unambiguous. Global mean temperature for January–August 2025 stood at 1.42 degrees Celsius (±0.12 degrees Celsius) above pre-industrial levels, and each of the 11 years from 2015–2025 is set to rank among the 11 warmest in the 176-year observational record (WMO 2025). The health cost is already measurable: heat-related deaths rose 63 per cent from the 1990s to 2012–2021, reaching an estimated 546,000 a year (Romanello et al. 2025). Heat also erodes economies. The International Labour Organization (ILO) projects that under a “Degrees” Celsius warming scenario, South Asia could lose 5.3 per cent of total working hours to heat stress by 2030 (ILO 2019). A World Bank report estimates that extreme heat results in productivity losses equivalent to nearly 31 million full-time jobs annually across the region, with economic output projected to decline by almost 7 per cent by 2050 (World Bank 2026).
As part of the Global Heat Health Information Network (GHHIN) South Asia Hub, this country synthesis focuses on India: the changing pattern of heat exposure, the populations and places most at risk, the institutions and policies now responding, and the practical approaches already being tested on the ground.
India’s historically stable relationship with its warm climate is shifting.
The rising temperature over India is turning a defining feature of the subcontinental civilisation into a complex developmental challenge. The average temperature over India rose by about 0.89 degrees Celsius during 2015–2024 compared with 1901–1930, with 2024 the warmest year on record since 1901 (Dhara et al. 2025; IMD 2025). This warming is uneven across seasons and geographies. While there is pronounced pre-monsoon warming over the north and summer warming across the Indo-Gangetic plains and central India, the north-western and central regions are experiencing frequent heatwaves. There has also been a significant rise in extremes, e.g., hottest days, warm days, summer nights, warm-spell duration, scorching days, and tropical nights (Bhattacharyya et al. 2025). As such, the population’s exposure to extreme heat has increased. The projected threefold increase in long-duration, large-area heatwave events at 1.5 degrees Celsius of global warming, the expansion of warming to the southern peninsula, and the rise in humid heat require concerted, systemic, and rapid institutionalisation of heat adaptation measures today.
Health impacts of extreme heat are increasingly experienced and documented.
India is experiencing growing public health impacts of extreme ambient heat, driven by increased exposure, demographic shifts, rapid urbanisation, epidemiological transitions, and existing socioeconomic inequalities. Almost 90 million Indians will be exposed to extreme heat at 1.5 degrees Celsius of global warming, the critical threshold recognized under the Paris Agreement as a key temperature limit for reducing climate risks (Lenton et al. 2023). India has recorded multiple heat-related mortalities since 1992, with most fatalities often linked to waning El Niño (NDMA 2019). Clinical evidence shows a greater representation of men and pre-existing conditions among heatstroke cases, with in-hospital mortality ranging from 11 per cent to 34 per cent (Ninan et al. 2020; J et al. 2020; Bhushan et al. 2026; Kalaiselvan, Renuka, and Arunkumar 2015). Among other heat-contributed health outcomes, evidence on cardiovascular and kidney diseases is increasing. Research has linked increases in ambient temperature with increased cardiovascular morbidity in adults—average 9 per cent excess risk with every degree temperature rise from 35 to 40 degrees Celsius (Fu et al. 2018). Known hotspots of chronic kidney disease are showing links to outdoor occupational heat exposure and high workloads with significant clustering among farmers, similar to other global clusters (Gifford et al. 2017; Venugopal et al. 2026). The synergistic impact of heat and air pollution exposure reportedly leads to higher PM2.5-related mortality (de Bont et al. 2025). Most consistent evidence now links antenatal heat exposure to adverse pregnancy outcomes, mainly preterm birth (3 per cent increase) and low birth weight (1 per cent increase), with generational consequences (4 per cent increase in low birth weight) in the high-emission scenario (Ai et al. 2025).
Occupational heat exposure and its impacts on life and livelihood are significant.
Occupational heat exposure and impacts are continuously being documented. Impacts of outdoor heat exposure and workload show a significant productivity loss (up to 5 per cent per 1 degree Celsius above Wet Bulb Globe Temperature of 26 degrees Celsius), and earning loss (up to 19 percentage points for each 1-degree Celsius Wet Bulb Temperature), highlighting the need for a calibrated work-rest schedule and basic water, shade, rest and cooling provisions (Sahu, Sett, and Kjellström 2013; Das and Somanathan 2024). The workers’ heat stress, in the northeast, could be minimised with a calibrated work-rest schedule of 50 and 20 minutes, and 35 and 22 minutes, for 29–30 degrees Celsius and 31–32 degrees Celsius, respectively (Pal and Patel 2026).
Local and individual vulnerabilities and adaptive capacities modulate health impacts.
Urban heat islands intensify heat exposure in Indian cities, with anthropogenic forcing and land-use changes amplifying temperatures beyond regional climate trends. In a study of 44 major Indian cities, the difference in land surface temperatures between urban and the surrounding rural areas was more than 2 degrees Celsius for most cities across all seasons (Raj et al. 2020). The built environment at the household level allowed for continued heat exposure by remaining 5–6 degrees Celsius higher in cities (Mukhopadhyay, Weitz, and Das 2021). Social inequalities directly and indirectly contribute to higher impacts. Lower-income wards, migrant workers, and rural women in different study settings have experienced higher heat burden, highlighting the role of basic provisions, environmental justice, and gender equality (Mitchell, Chakraborty, and Basu 2021). A recent nationwide assessment of heat-health risk found that 57 per cent of India’s 734 districts face high to very high heat risk (Prabhu et al. 2025). Multiple sub-national assessments are also carried out; however, evidence of their role in reducing health impacts is yet to emerge.
Core heat governance and policy responses are established and strengthening.
India’s national heat governance has undergone a profound evolution, moving from reactive, post-disaster response to proactive risk reduction. Guided by early state- and city-level innovations, the National Disaster Management Authority has successfully scaled this architecture across the country with Heat Action Plans (HAP) prepared by 23 states, 195 districts, and 64 cities based on its guidelines (NDMA 2026). Additionally, heatwaves were declared a nationally notified natural disaster in August 2026.
Under the Ministry of Health and Family Welfare’s National Programme on Climate Change and Human Health (NPCCHH), India’s public health system is institutionalising heat-health adaptation. Chief advancements are digitisation and expansion of the National Heat-Related Illness and Death Surveillance, and formalisation of health facility and ambulance preparedness with the operationalisation of heatstroke management units to manage severe heat-related illnesses in line with the “cool first, transport second” principle. It is sustained by massive, continuous capacity building efforts among health professionals, mobilisation of frontline health workers for awareness, and funding provisions.
On the meteorological front, the India Meteorological Department has refined early-warning precision through high-resolution Geographic Information System (GIS)-based forecasting, colour-coded messages, and experimental heat-index forecasting. These forecasts serve as triggers for HAPs and are bolstered by active collaboration among the government, civil society, and academic institutions.
India’s heat adaptation is expanding, but institutionalisation and impact assessments remain uneven.
Population, household, and individual-level heat adaptation measures are being tested and adopted across India. Model demonstrations of passive and active cooling solutions promise substantial temperature reduction, e.g., cool roofs (up to 5 degrees Celsius), cooling stations (up to 12 degrees Celsius), and green spaces (up to 6–8 degrees Celsius) (Garg et al. 2016; Jha et al. 2024; Shah, Garg, and Mishra 2021; Limaye, Kapoor, and Tiwari 2024). However, the current body of evidence on adaptation to extreme heat in India has largely focused on documenting, with occasional estimation of exposure reduction, and hardly any assessment of their effectiveness and impacts in terms of health outcomes (Takacs et al. 2024).
The parallel development of the collaborative ecosystem of research institutes, civil society and community-based organisations, development partners, philanthropic foundations, and private-sector actors has sought to fill technical, implementation, and field-level knowledge gaps through policy analysis, piloting of cooling solutions, social protection, training, tools, and knowledge products.
Scaling heat action through multi-sectoral integration and local governance
Heat action needs to be mainstreamed beyond its current concentration within disaster management and a single health programme. As the critical determinants of heat-health risk are influenced by upstream drivers—access to water, cooling, shade and rest—alignment with urban planning, labour, agriculture, water and power is essential to address the underlying vulnerabilities and reduce fragmented responses (Pillai and Dalal 2023; WHO Regional Office for Europe 2026). It will require adapting existing coordination mechanisms to include these sectors, supported by joint planning processes, interoperable data systems, and clearly defined roles and accountability across departments.
Unlocking finance for long-term heat adaptation
With dedicated finance provisions in disaster mitigation and relief funds, further opportunity lies in spearheading heat action. Moving from ad-hoc allocation towards convergent and blended financing, drawing on central funds, municipal budgets, and private and climate finance, will support investment at a greater scale and with greater continuity.
Strengthening institutional capacities and coordination mechanisms
The impacts of extreme heat, as well as scientific evidence of its effects, are emerging at an unprecedented speed. With a lack of prior tested knowledge and strategies to measure, design, implement and assess, building individual and institutional technical capacities requires a steep learning curve, dedicated financial resources, and strong leadership. Continuous translation of evidence into policy, and of field implementation into feedback to adopt effective measures and prevent maladaptation, is critical. It calls for strengthening of research, and data management and data sharing capacities. Expanding the scope of research to humid heat, chronic heat exposures, and personalised risk assessment will be relevant.
Health-centric heat action planning, implementation and evaluation
Health outcomes remain largely insufficiently integrated into the planning, implementation and evaluation of heat adaptation measures. It reflects persistent methodological, data, and financing shortfalls. Early warning systems, risk communication, health preparedness, built environment, and community measures fail to fully access, utilise, and generate health data, and often lack physiological and epidemiological grounding.
Compounding this, data related to health surveillance, civil registration, census, meteorological parameters, greenhouse gas (GHG) emissions, expenditure, and implementation remain fragmented, constrained by inadequate digital infrastructure and limited data interoperability across systems and capacities. Addressing this fragmentation requires integrating a monitoring and evaluation framework into HAPs and Heat-Health Action Plans (HHAPs) that clearly defines process, output, and health-outcome indicators, allowing programmes to assess not only whether actions were implemented, but whether they reached intended populations and reduced heat-related morbidity and mortality.
Strengthening the health system’s capacity across the full exposure-impact continuum.
It also requires strengthening the health system’s capacity to prevent, detect, manage, measure, and communicate heat-related morbidity and mortality. Implementation of case definitions, medical protocols, and diagnostic disease codes is critical. Effective utilisation of health sector-led multisectoral taskforces under the NPCCHH, sustained funding, and trained human resources remain the most consequential challenges (Chaudhry, Mukhopadhyay, and Guin 2025). State Action Plans on Climate Change and Human Health (SAPCCHHs) and, consequently, HHAPs, have remained severely underfunded and disconnected from major streams of disaster or climate-oriented financing. With India’s National Adaptation Plan under development and HHAPs approaching revision, there is an opportunity to reposition heat-health action as a core health-system and adaptation priority.
India’s heat response has made important gains, but the next frontier is to continuously translate and calibrate these advances into sustained, system-wide resilience. Over time, long-term resilience will depend not only on responding better to extreme heat but also on building systems that can anticipate, prevent, and reduce the health impacts of chronic and humid heat. As the world approaches a potential overshoot of 1.5 degrees Celsius of warming in the coming years, the effectiveness and limits of adaptation will come under strain. Adaptation, therefore, must also be complemented by deep, ongoing climate mitigation to achieve sustained reductions in heat-related risk (UNEP 2026).
The GHHIN South Asia Hub aspires to support these priorities by convening stakeholders, strengthening the regional evidence base, facilitating knowledge exchange, and building capacities for heat-health action. This can help India translate emerging evidence into practical, scalable and context-specific approaches to reducing the health, livelihood and socioeconomic impacts of extreme heat.
Extreme heat is increasingly being recognised worldwide as a major and multifaceted climate risk to public health and productivity. The increase in frequency, intensity and duration of extreme heat worldwide is largely driven by rising global temperatures, whereas its risks are driven by rapid urbanisation, and existing health vulnerabilities and socioeconomic inequalities. The warming signal is unambiguous. Global mean temperature for January– August 2025 stood at 1.42 degrees Celsius (±0.12 degrees Celsius) above pre-industrial levels, and each of the 11 years from 2015 to 2025 is set to rank among the 11 warmest in the 176-year observational record (WMO 2025). Since the 1990s, heat-related mortalities have increased by 63 per cent, averaging 546,000 deaths per year over the period 2012–2021 (Romanello et al. 2025). Under current policies and near-term trajectories, exceeding 1.5 degrees Celsius of global warming is now widely considered unavoidable. However, the magnitude and duration of this overshoot remain contingent on the pace and scale of mitigation and adaptation action (UNEP 2026).
Cities in Asia, particularly Southeast Asia, are increasingly exposed to hazardous humid extreme heat events (Agarwal, Nagpure, and Ramaswami 2024). By 2070, around 520 million people across the region could experience at least one month of dangerous heat each year. The risk is particularly pronounced in cities, where dense urban areas can remain more than 10 degrees Celsius hotter at night than the surrounding countryside, intensifying heat exposure and limiting overnight recovery (World Bank 2026). Under a 1.5 degrees Celsius warming scenario, southern Asia could lose 5.3 per cent of total working hours to heat stress by 2030, equivalent to approximately 43 million full-time jobs (ILO 2019). In India, one of the largest and most populous countries in South Asia, over 50 per cent of Indian districts, which are home to nearly threequarters of the population, are already facing high to very high heat risk (Prabhu et al. 2025). Similarly, Bangladesh has experienced a 1.1 degrees Celsius increase in maximum temperatures since 1980, while feels-like temperatures have risen by 4.5 degrees Celsius, contributing to growing physical and mental health burdens, including heat-related anxiety and depression (World Bank 2025).
Rising global temperatures have accelerated changes in the cryosphere (places on Earth where water is frozen solid), particularly in high-mountain regions, leading to reductions in snow cover, as well as glacier retreat and permafrost degradation (IPCC 2019). In the Himalayan countries of Nepal and Bhutan, these impacts threaten water security, ecosystems, and mountain livelihoods (Adler et al. 2022). The low-lying regions of these high-altitude countries are increasingly experiencing extreme heat, with temperatures in some areas now regularly exceeding 40 degrees Celsius (Bhandari et al. 2025).
India’s warm climate shaped its settlements, agriculture, and culture, sustaining a livable equilibrium across a vast civilization. Anthropogenic climate change is now pushing ambient heat past that balance, turning a defining feature of the subcontinent into one of its gravest threats. Rising temperatures are reshaping exposure to dry and humid heat across India’s regions, seasons, and households, altering how people live, earn, and move. With episodic extremes, emerging chronic heat exposure not only inflicts direct and indirect health consequences but also drives cascading, compounding hazards that affect public health through institutions, sectors, societies, and political stability (Shaw et al. 2022; Birkmann et al. 2022). The burden does not fall evenly; existing socioeconomic inequalities, as well as the direction and inclusivity of India’s development, will shape the extent of vulnerability and adaptive capacities. Governments have responded with policy measures, such as heat action plans, early warning systems, and health-system preparedness that support heat adaptation. Civil society groups, research institutes, and community organisations are working alongside them to close knowledge and implementation gaps. With continued global warming, heat adaptation in India will have to navigate an increasingly difficult terrain: unpredictable impacts, human survivability limits, inadequate mitigation at both global and local levels, unresolved questions of long-term institutional resilience, and the limitations of adaptation itself, while still targeting sustainable development (UNEP 2026). This report synthesises the current evidence on India’s rising heat exposure, its foremost health impacts, the status of the country’s heat governance and policy responses, and potential future trajectories.
Historical temperature change
India has witnessed an average temperature rise of around 0.7 degrees Celsius during 1901–2018 driven by anthropogenic activities (Krishnan et al. 2020). This warming is neither seasonally nor spatially uniform: assessments of the more recent sub-period 1986– 2015 reveal an accelerated average decadal warming rate of 0.15 degrees Celsius with the pre-monsoon season (March–May), the season usually prime for heatwaves, warming the fastest at 0.26 degrees Celsius per decade. Spatially, warming has been most concentrated over north and northwest India (exceeding average 0.2 degrees Celsius per decade), while the southern peninsula and west coast have warmed more slowly (below 0.1 degrees Celsius per decade). The pre-monsoon season over north India has shown predominant warming of more than 0.5 degrees Celsius per decade, while summer warming is largely recorded in the Indo-Gangetic plains and adjoining central India, with a smaller, uniform postsummer rise across the country. The frequency of very warm nights has increased in more than 70 per cent of Indian districts in the last decade (2012- 2022) compared to the baseline (1982-2011). The frequency, total duration, and intensity of heatwaves during the hot summer months (April–June) are increasing over the central and north-western parts of India, influenced by the tropical Indian Ocean and central Pacific sea surface temperature anomalies with a noticeable increased frequency during El Nino events. As such, 2024 was the warmest year on record since 1901 (IMD 2025). Moreover, relative humidity has also risen by up to 10 per cent on average during March-April-May-June in previously drier regions such as North India in the same period (Prabhu et al. 2025).
Present and future heat hazard
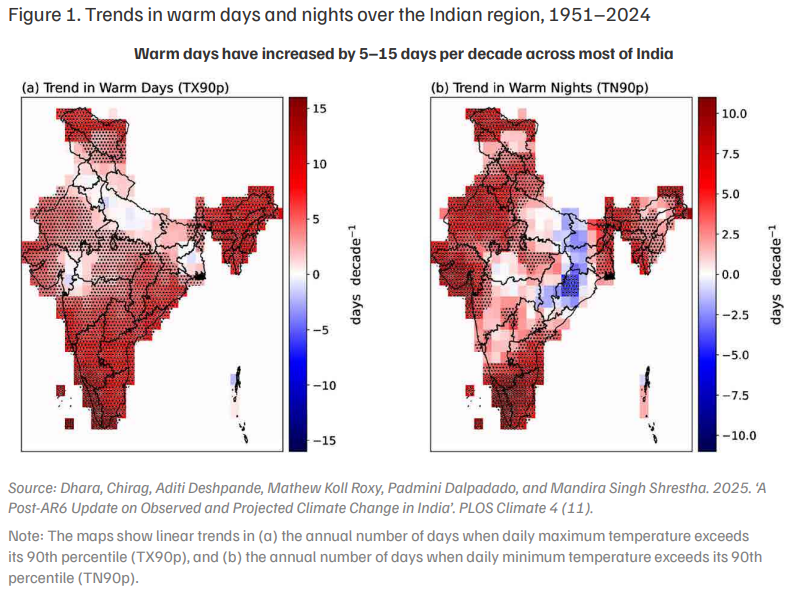
India’s land warming for 2015–2024, relative to a 1901–1930 baseline, has reached approximately 0.89 degrees Celsius as per more recent observations (Dhara et al. 2025). Warm days have increased by 5–15 days per decade, and warm nights are rising the fastest over Rajasthan, Gujarat, and the southern and northeastern states (Figure 1). Besides, there is significant rise in extremes such as hottest days, summer nights, warm-spell duration, scorching days, and tropical nights (Bhattacharyya et al. 2025). Compound heat-drought events have also grown measurably more frequent since the 1980s, particularly in urban areas.
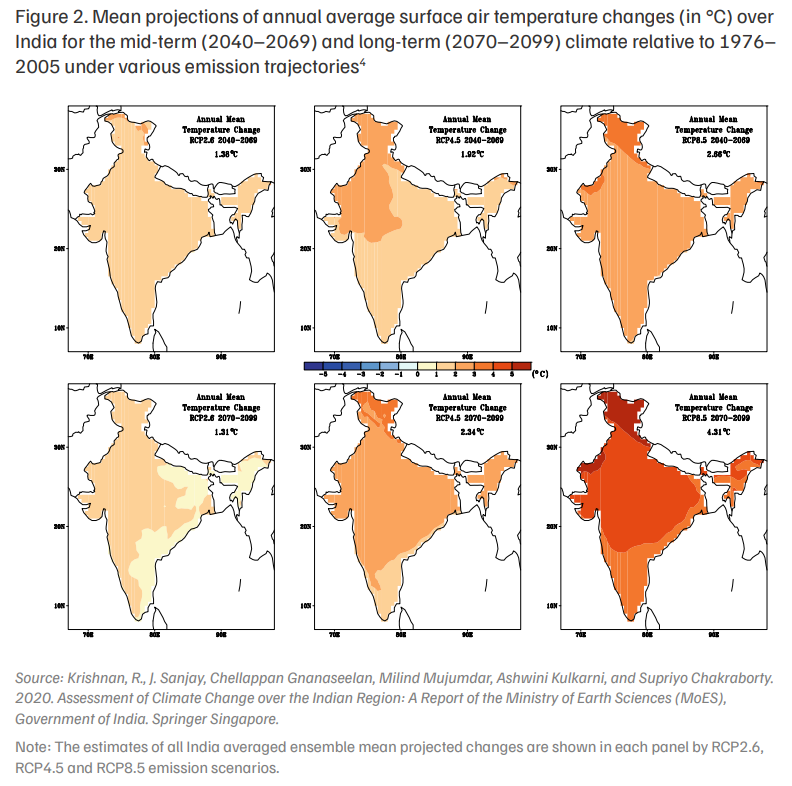
Projections indicate this intensification will continue and accelerate. Under CORDEX South Asia and CMIP5 model ensembles3, the projected mid-term annual warming exceeds 1 degree Celsius over most parts of the country, with higher warming, exceeding 2 degrees Celsius projected in the north-west and north India under the medium Representative Concentration Pathways 4.5 (RCP4.5) emission scenario. (Dhara et al. 2025).
Mean annual warming by end-century (2070–2099) is projected to exceed 4 degrees Celsius across most of India under a high-emission (RCP8.5) pathway, with summer heatwave frequency rising from roughly one event per season historically to 3.0–3.5 events per season, and total heatwave duration extending to 25–35 days per season nationally, with northwest India projected to see duration increases exceeding 40 days per season (Krishnan et al. 2020). As shown in Figure 2, more recent CMIP6-generation projections, framed against Paris Agreement thresholds, estimate a threefold increase in long-duration, large-area heatwave events at 1.5 degrees Celsius of global warming, rising to fivefold at 2 degrees Celsius, alongside a doubling in the likelihood of dangerous humid-heat stress across the Indo-Gangetic plains. Notably, both assessments flag southern India, historically less heatwave-affected, as an emerging hazard frontier by mid-to-late century
National and subnational heat exposure and health impacts
India is experiencing growing public health impacts of extreme ambient heat, driven by increased exposure, demographic shifts, epidemiological transitions, and existing inequalities. Almost 90 million Indians will be exposed to extreme heat at 1.5 degrees Celsius global warming, the Paris Agreement target, and this may rise to 600 million at 2.7 degrees Celsius global warming, the projected temperature increase by end of century under current policies (Lenton et al. 2023). This growing exposure is expected to substantially increase heat-related mortality, with about a 10 per cent increase in the current death rate by 2100 (Jina et al. 2019). An estimated additional 0.12 million deaths among adults aged over 65 years may occur at 2 degrees Celsius of global warming, rising to 0.26 million under a 3.7 degrees Celsius scenario by the middle of the century in India. (Romanello et al. 2023). Urban areas are at the forefront of this crisis. Between 1983 and 2016, India accounted for more than half of the global population exposed to extreme urban heat stress of wet bulb globe temperature (WBGT) >30 degrees Celsius, with 17 of the world’s 50 most heat-stressed cities located in the country. The drivers of urban heat exposure also vary across cities: in Delhi, nearly 75 per cent of the increase in heat exposure is attributable to rapid urbanisation, whereas in Kolkata, urban warming and urbanisation contribute almost equally to the observed increase in heat stress (Tuholske et al. 2021).
Between 1992 and 2019, India reported about 25,958 heat-related mortalities (NDMA 2019a). Years influenced by strong El Niño events have witnessed the highest spikes in mortality: more than 3,000 deaths in 1998 across northern plains regions and more than 2,000 in 2015 in the south-western region. Between 2021 and 2024, about 71,880 suspected heatstroke cases and 381 heatstroke deaths were reported under the National Heat-Related Illness and Death Surveillance (NHRIDS) (Patel and Shrivastava 2025). In 2026 (March 1-July 26), the figure stood at 4,853 heatstroke cases and 20 deaths (MHA 2026). These estimates of heat-related illnesses (HRI) seriously underestimate the greater and variable impact of heat exposure on the population.
A comprehensive 10-city study estimated an increase of about 14.7 per cent (95 per cent CI, 10.3-19.3 per cent) in daily mortality for daily mean temperature above the 97th percentile for 2 consecutive days compared to non-heatwave days, reflecting as about 1,116 annual heatwave-attributable deaths cumulatively (de Bont et al. 2024). When extrapolated nationwide, approximately 3,400 excess deaths are estimated to occur following a single day of nationwide exposure, discounting population, disease, and land-use dynamics (Narang and Gadgil 2026).
Regional analyses reveal substantial geographic heterogeneity in heat-mortality relationships. The 10-city study reported a large variation in relative mortality risk, with Ahmedabad reporting the highest at 24.9 per cent (95 per cent CI, 21.7–28.2 per cent), followed by Varanasi at 23.1 per cent (95 per cent CI, 16–30.7 per cent). While Bengaluru at 5.7 per cent (95 per cent CI, 1.6–9.9 per cent) and Mumbai at 3.4 per cent (95 per cent CI, 0.8-6.1 per cent) were shown to have a lower relative risk at temperatures above the 97th percentile for two consecutive days (de Bont et al. 2024). The excess mortality risk rose sharply above 42–45 degrees Celsius influenced by local climate and heat-stress metrics. Ahmedabad documented excess all-cause mortality associated with the 2010 Ahmedabad heatwave, establishing baseline evidence that led to India’s first heat action plan (Hess et al. 2018). A 30-year time series study released subsequently demonstrated a substantial increase in mortality, 9.56 per cent (95 per cent CI, 6.64–12.56 per cent), at maximum temperatures exceeding 42 degrees Celsius, from 1987 to 2017, in Ahmedabad (Wei et al. 2021). Nagpur reported a relative risk of 1.5 at temperatures exceeding 45 degrees Celsius (Dutta et al. 2020). Another study in Varanasi recorded 5.61 per cent increase in mortality per unit temperature increase in summer, with daily mortality rising up to 12.02 per cent (95 per cent CI, 4.21-19.84 per cent), due to heatwaves during 2009-16 (Singh et al. 2019). A recent study utilising an indigenous heat stress index based on contextualized WBGT, i.e. India Heat Index (IHI), sought to analyse daily all-cause mortality in three cities across different climate zones—Delhi (semiarid), Varanasi (humid subtropical), and Chennai (tropical wet and dry). It reported an increased allcause mortality risk of 8.1 per cent (95 per cent CI, 6.0–10.3 per cent), 5.9 per cent (4.6–7.2 per cent), and 8.0 per cent (1.7–14.2 per cent) in Varanasi, Delhi, and Chennai, respectively, during “sweltering” days (above 90th percentile of the IHI) compared to “comfortable” days (below 25th percentile) over the last decade (Choudhary et al. 2023).
Extreme heat and health outcomes
Extreme heat is a public health threat multiplier, amplifying the risk of adverse health outcomes through direct and indirect effects on the human body. Direct exposure can disrupt thermoregulation and cause HRI, while heat stress can also exacerbate existing cardiovascular, renal, respiratory, and other non-communicable conditions through multiple physiological pathways, contributing to increased hospital admissions and heat-related mortality.
Heat-related illnesses
In India, direct health impacts of environmental heat exposure are not a recent emergence but have a documented historical presence as a military malady (Griffiths 2004). In fact Indian summers have shaped architecture, agriculture, culture, and governance over millennia, whether through stepwells, fenestrated windows (jali), cotton textiles, millet crops, or the shifting of national capitals. With increasing climate change impacts, the risk and incidence of HRI and other heat-contributed illnesses are increasing.
The evidence on HRI distribution comes largely from two types of settings in peer-reviewed journals: the high prevalence of occupational burden, where workers bear disproportionate exposure under conditions of inadequate protection and systemic under-preparedness, and the sporadic occurrence of acute clinical burden triggered by a perfect concoction of exposure, vulnerability, and adaptive capacity at the population scale. Among occupational groups, about 59 per cent and 37 per cent of >200 workers in Gujarat and West Bengal, respectively, reported moderate to high perceived risk of heat stress and HRI (Barman et al. 2024; Dutta et al. 2015). About 40 per cent of 400 agricultural workers in Tamil Nadu reported experiencing HRI in another study (Shakthi Chakravarthy, R, Peter, et al. 2025). Clinically, inpatient and emergency units treating severe HRI have observed a higher proportion of males of different age ranges, and individuals with pre-existing conditions among cases that present with universal neurological impairment and multi-organ dysfunction syndrome. In hospital mortality among severe HRI cases ranged from 11 per cent to 34 per cent across reported case series from Chennai, Vellore, Patna, Ahmedabad and New Delhi (Kalaiselvan, Renuka, and Arunkumar 2015; Ninan et al. 2020; J et al. 2020; Bhushan et al. 2026; Roy, Khatri, and Parikh 2019; Aggarwal et al. 2024). Hyponatraemia—sodium depletion beyond normal levels is the most common biochemical derangement reported. A few survivors of heatstroke have developed residual neurological deficits, suggesting extension of the burden beyond case fatality into long-term disability.
The 2024 Delhi heatwave constitutes a threshold event with over 270 citywide deaths, nine heatstroke admissions within a single 24-hour window at one hospital, and HRI incidence among physiologically heat-acclimatised individuals (Aggarwal et al. 2024; Titiyal et al. 2024; Bhushan et al. 2026). Collectively, the literature converges on shared vulnerability drivers for outdoor exertion: low education and awareness, absence of workplace protection, lack of cooling infrastructure, and underestimation of HRI in highrisk groups, suggesting that individual-level risk often reflects systemic and environmental deprivation rather than personal behaviour. Improved heatstroke survival in hospital settings over the years may be attributed to greater awareness and standardised rapid cooling protocols; yet the 2024 example demonstrates that such capacity remains wholly inadequate for heatwave surge scenarios, making integrated investment across occupational safety, clinical infrastructure, and climate-adaptive public health planning a matter of escalating urgency (Aggarwal et al. 2024; Titiyal et al. 2024).
Emerging evidence on other health outcomes
Heat exposure adds physiological stress on the cardiovascular system. A time-series study (2011– 2020) of non-optimal apparent temperature and 3,960 in-hospital cardiovascular mortality records showed that up to 9.1 per cent of the burden was heatattributable. Women over 60 were more vulnerable to heat than cold, and cerebrovascular mortality was more strongly associated with heat exposure (Shrikhande et al. 2023). Another large study involving 0.5 million death records found a 9 per cent excess risk on average with every degree of temperature increase from 35 degrees Celsius to 40 degrees Celsius for adults 30 years and older, with a steep rise in risk for those 70 years and older. Hot temperatures had a more immediate effect on overall mortality with the harvesting phenomenon—a sharp rise in fatalities among frail and severely ill individuals, followed by a drop, linked to a particular environmental exposure—compared to cold temperatures (Fu et al. 2018). In occupational settings, high cardiovascular strain from heat exposure is documented. Among rice harvesters exposed to 26–32 degrees Celsius WBGT, heart rate recovery was significantly impaired, and cardiovascular strain persisted (Sahu, Sett, and Kjellström 2013). There is a paucity of indigenous studies on heat stress affecting cardiovascular medical management and vice versa to compare with emerging global evidence.
Respiratory morbidity linked to heat has not been explored as an isolated exposure but more as a combined exposure with air pollution. The synergistic impact of both climate-related environmental risk factors was revealed with findings from 10 Indian cities showed an increase in PM2.5-related mortality from 0.8 per cent (95 per cent CI: −0.3–1.9 per cent) to 4.6 per cent (95 per cent CI: 2.9–6.5 per cent) per 10 micrograms per cubic meter (μg/m3 ) increments when temperatures shifted from the 75th to the 90th percentile (de Bont et al. 2025). This synergistic interaction is particularly concerning, given India’s dual burden of extreme heat and severe air pollution. It is especially concerning due to the early and continuous exposure among children (Etzel and Bhave 2023).
India contains endemic hotspots of chronic kidney disease of unknown aetiology (CKDu), which mainly affects rural agricultural and coastal communities. The CKDu clusters reported from Andhra Pradesh, Odisha, Maharashtra, Chhattisgarh, and Goa share epidemiological, clinical, and pathological similarities with those reported from countries in Central America, as well as Sri Lanka and Egypt (Gifford et al. 2017; Galhotra et al. 2024). An increasing number of studies highlight its possible association with recurrent heat exposure, occupation-linked physical exertion, and inadequate hydration. A study of 18–75 year old workers across 36 villages from the hotspot of Uddanam, Andhra Pradesh, affirmed the significantly higher heat exposure experienced among agriculture, brick kiln, and construction workers. Outdoor workers having heavy workload above 27.5 degrees Celsius WBGT and moderate workload above 28.0 degrees Celsius WBGT have been found to be twice as likely to have reduced kidney function than those with a similar workload but at lower heat exposures (Venugopal et al. 2026). In Bargarh, Odisha, farmers were found to experience significantly prolonged daily heat stress exposure, high agrochemical exposure, higher prevalence of dehydration, urinary tract infections, and reduced kidney function compared to labourers and other workers. Among workers with CKDu, farmers were the largest group exhibiting symptoms like those of heat stress nephropathy (Biswas et al. 2025). A higher risk of kidney stone was observed among steel workers engaged in moderate to heavy labour with at least three years of heat exposure compared to unexposed (Venugopal et al. 2020).
There is a paucity of evidence linking heat exposure to neurological and mental health outcomes in India. Recent evidence from the Indian WHO-SAGE, a nationally representative household survey, showed that an adult exposed to a mean Wet Bulb Temperature (WBT) above 27 degrees Celsius for two consecutive days is 2.6 percentage points more likely to have suffered from severe depression—an acute, short-term mental health impact (Fritz 2026). Heat exposure during agricultural work, increased cognitive difficulties, and sleep disturbances were linked to poorer mental health among rural populations, while urban populations remained unaffected. The Longitudinal Aging Study of India showed a significant association between heat exposure and worsening self-reported feelings of depression, fatigue, fear, and decreased life satisfaction among older adults (Wang, Li, and Rajagopalan 2025). The analysis also indicated that access to cooling devices in rural areas and access to on-site water are beneficial for urban residents. Among heat-exposed workers in South India, risks of climate anxiety, stress, and mental fatigue were at least double (KG et al. 2025).
Evidence on the impact of extreme heat on other health domains, e.g., reproductive and child health; digestive, respiratory, and metabolic systems; pharmacodynamics; and health service delivery, is minimal. Humid heat and chronic heat exposures have yet to enter public health discourse. The indirect ways of heat’s influence on health outcomes, such as through cascading and compounding exposures e.g., drought, wildfire, ozone pollution; through food and water insecurity and altered disease dynamics that lead to foodborne, waterborne, and vector-borne diseases; as well as through accidental injuries; are not covered in this document.
Extreme heat in occupational settings
Beyond specific disease outcomes, heat exposure imposes a substantial, quantifiable burden on labour capacity and household income in India, with direct implications for healthcare expenditure and access. India, most affected by heat stress, had lost 4.3 per cent of working hours by 1995 and is projected to lose 5.8 per cent in 2030, largely in agriculture and construction (ILO 2019). Heat exposure in 2024 resulted in the loss of 247 billion potential labour hours nationally and 419 hours individually, 124 per cent higher than the 1990–1999 baseline, with a potential income loss of US$194 billion; agriculture accounted for 66 per cent of these losses and construction for 20 per cent (Romanello et al. 2025).
Occupational heat exposure represents one of the most severe and scientifically well-researched health impacts of heat in India. In Tamil Nadu, informal outdoor workers with heat exposure consistently above safe thresholds faced a 1.4-fold increase in the risk of productivity loss (Venugopal, Latha, and Shanmugam 2026) during 2021–2023. For urban informal workers of Delhi, rising temperature showed negative impacts on both gross and net earnings. Each 1-degree Celsius increase in WBT was associated with a fall of 13 and 19 percentage points in gross and net earnings, respectively (S. Das and Somanathan 2024) in 2019. Among the rice harvesters of West Bengal, productivity loss was up to 5 per cent per 1 degree Celsius above WBGT of 26 degrees Celsius, and recovery from cardiac strain was slow. Migrant brick kiln workers endure heat that reaches the upper limits of human tolerance (up to 45 degrees Celsius ambient temperature in hot months and 52 degrees Celsius radiant heat from brick kiln furnaces over many years), leading to severe cardiac strain and physiological exhaustion (Lundgren-Kownacki et al. 2018). This exposure resulted in a linear decline in productivity of approximately 2 per cent per 1 degree Celsius above 34.9 degrees Celsius, as workers adopt self-pacing strategies to manage the extreme thermal load (Sett and Sahu 2014).
Some of the earliest physiological evidence documenting the independent effects of environmental temperature and work severity on the dynamic balance of body temperature regulation among young male farmers comes from environmental chamber experiments. At 34 degrees Celsius WBGT exposure, the measured tolerance time was 55 minutes, which decreased by 4–5 minutes at 38 degrees Celsius WBGT, and by an additional 2–4 minutes per 1-degree Celsius increase in WBGT beyond that (Nag, Nag, and Ashtekar 2007). Among steel metal, ceramic and stone quarry workers of western India, the critical heat tolerance limit was reached when the core body-toskin temperature gradient narrowed significantly from 5.8 degrees Celsius to 2.5 degrees Celsius, significantly limiting heat dissipation through the skin and increasing cardiovascular efforts. This peripheral adjustability threshold signals the body’s maximum capacity to dissipate heat, which workers primarily manage through self-pacing strategies to keep core temperatures within a safe 38 degrees Celsius range (Nag, Dutta, and Nag 2013). More recently, a study in rice plantation workers of the northeast estimated that to minimise heat stress, at 29–30 degrees Celsius and 31–32 degrees Celsius, work-rest durations should be 50 and 20 minutes, and 35 and 22 minutes, respectively (Pal and Patel 2026). These findings collectively underscore the need for evidence-based interventions to reduce critical physiological strain that outstrips natural thermoregulatory defences. Recent modelling and field-level studies are exploring ways to study and account for physiological changes in the Indian population, whether it is the India Heat Index, a contextualised version of the WBGT (Choudhary et al. 2023), or calibrating heat stress (Justine et al. 2023; R.R. Kumar et al. 2026).
Extreme heat and key vulnerabilities
Heat-health vulnerability in India is multidimensional, arising from the interaction of physiological susceptibility, environmental exposure, socioeconomic conditions, and institutional capacity that shape people’s ability to adapt to acute and persistent extreme heat. These determinants vary across populations and places, producing substantial differences in heat exposure and health risk. The evidence below examines vulnerability at the individual, built-environment, and socioeconomic levels, followed by the status of heat-health vulnerability and risk assessments and evidence on heat adaptation across populations and geographies.
Physiological vulnerability
Evidence on age- and gender-specific health impacts remains sparse. Heat drives disproportionate mortality in India’s elderly, with all-cause deaths rising 5.9–8.1 per cent on extreme-heat days; worse in humid subtropical Varanasi compared to Delhi or Chennai (Choudhary et al. 2023). When compounded at the individual level, Kolkata’s slum-dwelling urban elderly have been found to face a 4.3 times greater exposure to dangerous heat indices (≥45 degrees Celsius) than rural elderly, based on their activity levels. Conversely, only rural elderly women are four times more likely to experience dangerous HI levels during the hottest times of the day compared to elderly men, urban or rural (Weitz, Mukhopadhyay, and Das 2022a).
Heat was linked to a strong, immediate effect on mortality in a rural study that found total deaths rose 33 per cent and those from non-infectious diseases (cardiovascular, renal, respiratory) rose 57 per cent on extreme-heat days (Ingole et al. 2015). Notably, working-age adults (12–59 years), especially men—with the risk even greater for those working in an agrarian setting—have been found to show the strongest statistically significant heat-mortality association, with women and the elderly (60+) showing a non-significant elevated risk, potentially contrasting with high urban vulnerability among the elderly (Ingole et al. 2012). Children in India are also experiencing high heat exposure, vulnerability, and consequent increase in projected mortality (UNICEF 2026). Newborns are particularly vulnerable when institutional measures are inadequate to prevent heat exposure and provide cooling (Kakkad et al. 2014).
Emerging evidence from India concurs with the global evidence that foetal development is highly sensitive to temperature variations, and that heat exposure adversely affects pregnancy outcomes. Most consistent evidence comes for preterm birth (PTB) and low birth weight (LBW). Annual temperature rise (2001–2010) has been found to be responsible for about 3 per cent of all cases of babies born with an extremely LBW (Ai et al. 2025). A more recent analysis of total births reported in the National Family Health Survey (2015–20) showed that each additional day of consecutive high wet-heat exposure (IHI >90th percentile) throughout pregnancy was associated with a 1 per cent increase in odds of LBW (Vincent et al. 2026). Further, an analysis of trimester-wise heat exposure showed increased odds of PTB (3 per cent) in the first trimester, and LBW (1 per cent) in the second. Regionally, pregnant mothers from middle and lower Indo-Gangetic plains exposed to extreme heat (27.3–29.9 degrees Celsius) have been found to be twice as likely to deliver preterm compared to those experiencing normal temperatures (25.9–26.5 degrees Celsius), regardless of economic background (Samal et al. 2026). In the high-emission scenario, there can be a 4.31 per cent increase (95 per cent CI, 3.00–5.61 per cent) in the prevalence of low birth weight at the current fertility rate, suggesting generational impacts that warrant strengthening of maternal care (Ai et al. 2025).
High occupational heat exposure was associated with twice the odds of miscarriage and adverse outcome at birth among a cohort of pregnant women experiencing heat stress exceeding the threshold for safe manual work in Tamil Nadu. In Bihar, a positive association was found between exposure to extreme temperatures and stillbirths, with 7 per cent increased risk at 35 degrees Celsius, possibly due to immediate and delayed harmful effects (Yadav and Ranjan 2026). In Nagpur, 2nd-trimester heat exposure was uniquely associated with a study’s highest site-specific risk for preterm birth, and 3rd-trimester exposure with a high risk of gestational hypertensive disease, highlighting acute regional vulnerability to ambient thermal stress (Shankar et al. 2023).
Role of built environment
Urban heat islands (UHI) intensify heat exposure in Indian cities, with anthropogenic forcing and land-use changes amplifying temperatures beyond regional climate trends. In a study of 44 major Indian cities, the difference in land surface temperatures between urban and the surrounding rural areas showed a mean daytime surface UHI intensity, indicating the relative temperature difference, of more than 2 degrees Celsius for most cities across all seasons (Raj et al. 2020). In Delhi in particular, the urban-rural difference for duration and intensity of heatwave appears to increase at least by 2 days in future, and to 45 degrees Celsius in the short-term (2021-2045) to 49 degrees Celsius in far future (2081-2100), indicating a significant compounded heat exposure for the capital's population (Sharma et al. 2019). This differential exposure translates into even higher indoor temperatures in urban households, especially in crowded, low-resource settings in Kolkata and Ahmedabad (Weitz, Mukhopadhyay, and Das 2022b; Ranadive et al. 2021). It demonstrates that UHI affects not only outdoor exposure but also indoor thermal environments where residents spend most of their time.
A study conducted in Kolkata in the summer of 2019 found that heat index (HI) levels inside urban slum dwellings were 5.29 degrees Celsius higher than those outdoors (Mukhopadhyay, Weitz, and Das 2021). Dangerously high heat and humidity persisted for an average of about 9 hours a day in urban slum dwellings, compared to 2 hours in rural houses, with notable night-time differences. During the coolest time of night, the interiors of urban and rural houses recorded a 6.4 degrees Celsius and 1.3 degrees Celsius higher HI than outdoors, respectively. Cement walls, clay tiles, corrugated tin roofs, fewer rooms, and crowding made urban slums dangerously hot, while the coolest village houses were found to have mud walls and thatched roofs. Similarly, a study conducted during summer 2016 in urban Ahmedabad recorded that the average on-scene HI at locations (indoors and outdoors) where patients with acute heat illnesses were picked up by emergency medical services was about 6.7 degrees Celsius higher than that measured at the nearest weather stations, suggesting that people were exposed to higher temperature than that reported officially (Ranadive et al. 2021).
Socioeconomic vulnerabilities
Social inequalities directly and indirectly contribute to vulnerability and adaptive capacity. In Delhi, lower-income wards have lower green coverage and higher heat burden, highlighting environmental injustice in heat exposure distribution (Mitchell, Chakraborty, and Basu 2021). It calls for sustainable and equitable combined long-term structural efforts at resilience building with emergency preparedness. In Telangana, prehospital emergency calls showed a higher incidence of HRI among Scheduled Tribes and rural low-income groups (Nadarajan et al. 2021). Migrant workers employed at brick kilns in Tamil Nadu face high heat exposure due to temporary housing without cooling, limited knowledge of local healthcare systems, language barriers, and fear of losing employment if they report heat illness. Their compounded vulnerability arises from occupational heat exposure, poor living conditions, and limited healthcare access (Lundgren-Kownacki et al. 2018).
Rural women face high heat exposure from agricultural work, domestic responsibilities such as cooking over fires, and limited access to cooling or rest during peak heat hours, while young males face high exposure on account of strenuous work conditions, highlighting the heightened risk due to gender roles (Deshpande et al. 2024; Bhushan et al. 2026).
India’s heat-health vulnerability and risk
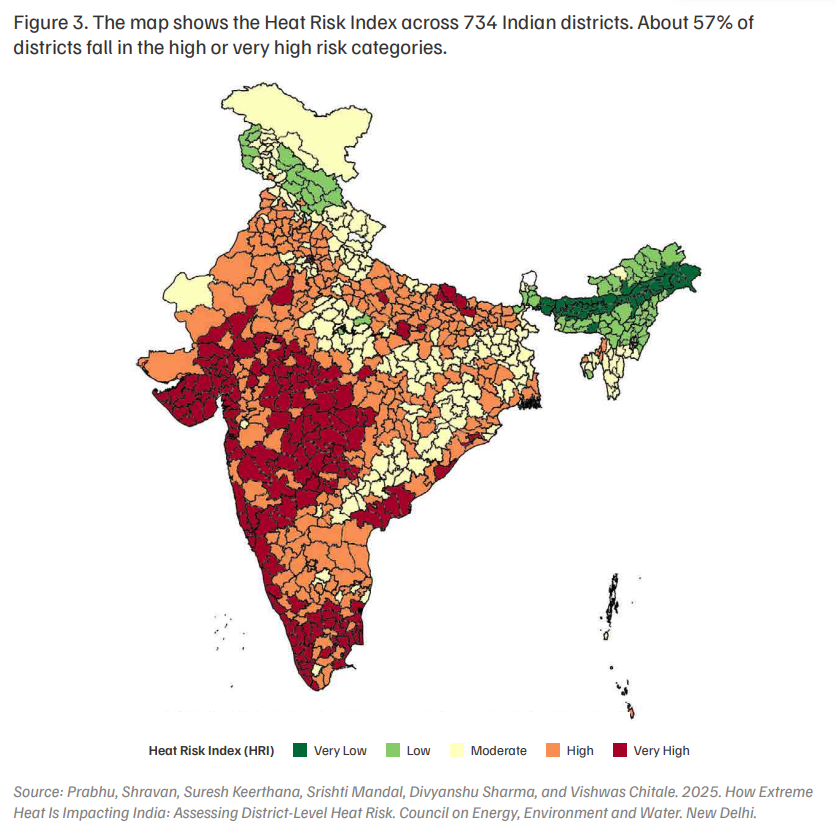
India’s heat-health vulnerability is largely an interplay among increasing, unpredictable hazards, existing inequalities, and inadequate responses. Varied climate zones, resource distribution, and population characteristics pose challenges to translating heat vulnerability research into concrete action. Various national heat vulnerability/risk assessments use different indicators and methods; while heat-health risk assessments are few. The first countrywide Heat Vulnerability Index identified 10 very-high-risk and 97 high-risk districts out of 640, and reported that the highest heat vulnerability was concentrated in central India, associated with low literacy and water, sanitation and amenities (Azhar et al. 2017). Another analysis involving 734 Indian districts found that 57 per cent face high to very high heat risk (Prabhu et al. 2025). It reported growing heat exposure not only due to an increase in very hot days but also on account of a greater increase in very warm nights, especially in districts with dense populations, and rise in relative humidity during the summer in the IndoGangetic plain. The resultant district-level risk was driven by socioeconomic and health vulnerabilities besides exposure (Figure 3). A recent heat-health risk assessment using the latest National Family Health Survey revealed that 6.6 per cent of India’s districts face high to severe heatwave risk. In South and Central India, it is predominantly hazard-driven, while in the northeast it is driven by socioeconomic and infrastructural vulnerability—a distinction with direct implications for action planning (Sahana et al. 2026). Multiple sub-national assessments have also been carried out; however, there is limited evidence of their implementation and effectiveness in reducing health impacts (Rathi et al. 2021). Systemic integration of these assessments into decision-making has yet to occur, likely due to unstandardised frameworks and a mismatch between predicted and observed outcomes (Qian and Liu 2025)
Heat adaptation and health outcomes
Population-, household-, and individual-level heat adaptation measures are being tested and adopted across India. A cool-roof intervention in rural and peri-urban Hyderabad achieved a mean indoor air temperature reduction of 2.1 degrees Celsius and a peak reduction of 5 degrees Celsius (Garg et al. 2016). Cooling garments worn by healthy construction workers resulted in significant reductions in heart rate and skin temperature (Ashtekar et al. 2019). Studies of urban green spaces show measurable local cooling effects in Indian cities. In Delhi, parks larger than 1.55 hectares with dense vegetation and water bodies reduced surrounding land surface temperatures by up to 8.28 degrees Celsius (Jha et al. 2024), while urban and peri-urban green spaces in Bengaluru and West Bengal recorded cooling differences of 2.23–6.89 degrees Celsius (Shah, Garg, and Mishra 2021; M. Das et al. 2025). Cooling shelters are also being established and assessed seasonally (Wu et al. 2024). Together, these findings support integrating an array of urban and built-environment measures into India’s heat response. However, the current body of evidence on adaptation to extreme heat in India has largely focused on documenting planning and implementation, with occasional estimates of exposure reduction, with hardly any assessment of health outcomes as an impact metric (Takacs et al. 2024).
Among the most critical institutional heat-health response strategies, heat action plans (HAPs), health system response, early warning systems, and built environment solutions are widely discussed and are mentioned below. HAPs are important tools for the institutionalisation of a heat-focused response that can contribute to reduced heat-related morbidity and mortality (Hess et al. 2018). However, substantial evidence of such impacts is yet to emerge.
As the world warms, the effectiveness and limits of adaptation will come under increasing strain (UNEP 2026). More frequent high-mortality summers, coupled with a larger swath of population exposed to increasingly hazardous hot, humid conditions, could test the limits of survivability (Vecellio et al. 2023). Hence, adaptation alone, without complementary deep mitigation strategies and long-term resilience measures, is insufficient in the context of heat-risk reduction. A lower global-emissions pathway could reduce India’s excess heat-related mortality by approximately 80 per cent, from 60 to 10 per 100,000, a gain no adaptation programme can replicate at scale (Jina et al. 2019). India’s coal dependence makes the stakes for public health especially consequential. Rising heat increases the demand for cooling, which, if largely met by coal, reinforces a cycle in which coal-fired power drives high exposure to air pollution and greenhouse gas (GHG) emissions, compounding the multiple adverse health impacts of heat and air pollution. Conversely, a city-level modelling in Ahmedabad showed that pairing renewable energy with cool roofs could avoid over 1,200 premature deaths annually through air quality improvement alone (Limaye et al. 2023).
India’s governance structure is federal in design, with tiered powers and functions distributed among the Union government, 28 states and 8 Union territories (UTs), and a third tier comprising urban and rural local bodies. Many climate governance-relevant domains, such as public health, agriculture, land, water, electricity, transport, and local governance are state subjects. In practice, however, the Union government occupies a stronger position. It commands a larger share of tax revenue, supplies much of the country’s bureaucratic and technical capacity, and shapes state policy through national schemes and centrally issued guidance. Climate governance in India has long adhered to this pattern (Pillai and Dubash 2023).
Heat governance has developed along similar lines, with national guidance largely defining implementation at the state, district and city levels. The variation across places is accounted for by differences in local governance—specifically, the structure and function of municipal bodies across cities and towns and that of gram panchayats in rural areas, local capacity, coordination arrangements between departments, and access to finance. The sections that follow trace this development.
Evolution of heat governance and policy responses at the national Level
The Indian state’s early response to heat can be characterised by post-disaster relief and recovery efforts, akin to the management of other natural disasters. Over the years, the states that witnessed frequent large-scale mass casualties and damage e.g. Odisha, began to formalise its post-disaster responses through policies such as notifying heatwaves as a local disaster to access disaster relief funds, provision of ex gratia compensations, and formalizing heat preparedness into action plans since 1999 (Odisha State Disaster Management Authority 2018).
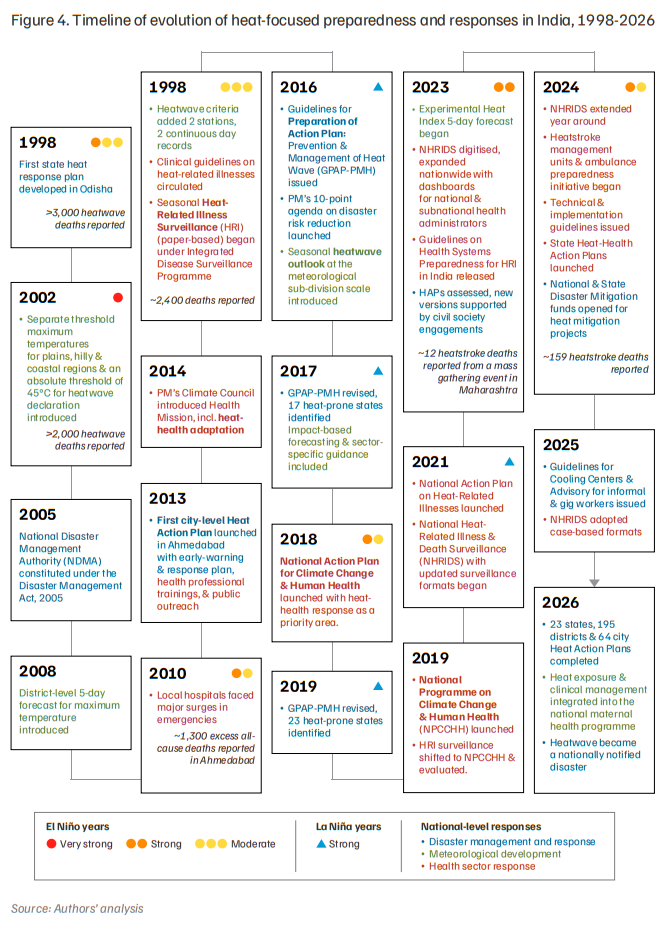
The 2010 heatwave was a watershed moment. The overburdened health facilities and excess deaths led the Ahmedabad Municipal Corporation to convene public health institutions, civil society organisations, and international academic partners to develop South Asia’s first Heat Action Plan (HAP) in 2013 (Ahmedabad Municipal Corporation 2019). With the establishment of a local threshold based on temperature-mortality analysis, adoption of simple colour-coded early warnings, use of various mass media for awareness and outreach, integration of intersectoral engagements, appointment of a municipal health officer as nodal officer, prioritisation of healthcare workforce capacity building and health facility preparedness, the plan shifted the focus from response to preparedness, and set the stage for public-health-oriented action that was closely informed by the health sector. Currently, the heathealth governance discourse is largely dominated by the disaster management, health, and meteorological departments (Figure 4).
Establishing heat-risk management framework
Nationally, extreme heat is governed within India’s disaster management architecture. The National Disaster Management Authority (NDMA), established under the Disaster Management Act of 2005 and chaired by the Prime Minister, is the country’s apex body for disaster management. It lays down policies, coordinates implementation, and recommends the allocation of funds (Government of India 2005). With the adoption of a 10-point agenda on disaster risk reduction in 2016, the response to extreme heat began to shift towards risk reduction (MHA 2023).
The NDMA has taken substantial measures to drive heat-risk reduction efforts by developing guidelines and facilitating the development of HAPs for states and cities in the 23 heat-prone states through capacity building and stakeholder engagement. The National Guidelines for Preparation of Action Plan: Prevention and Management of Heat Wave were launched in 2016, with revisions in 2017 and 2019. It led State and District Disaster Management Authorities to draft and implement localised HAPs (NDMA 2019b). A rapid diffusion of HAPs across different levels of the government followed.
By the early 2020s the national architecture for heat governance was largely in place. With the early onset of summer in 2022 and heat-related mass casualties in summer 2023, attention was brought to the effective implementation of HAPs. A review of 37 HAPs highlighted the need to assess local population vulnerabilities and capacities for better response and resource allocation (Pillai and Dalal 2023). HAPs were also kept devoid of dedicated funding and formal legal mandates, which shaped the incentives available to implementing agencies. In 2022, the NDMA introduced the National Disaster Mitigation Funds and State Disaster Mitigation Funds with a small provision for local heat-related response efforts. Meanwhile, a guide on Alternate Roof Cooling Solutions for house owners and the Guidelines for Cooling Centres were released (NDMA 2021, 2025b). In 2025, an advisory on protecting informal and gig workers was issued, likely in response to advocacy that had developed around heat and labour (NDMA 2025a).
State-level responses were being parallelly reinforced. By 2025, around 12 states considered heatwaves as a locally notified disaster. In August 2026, based on the 16th Finance Commission’s recommendation, India declared heatwaves as a nationally notified natural disaster, and added it to the operational guidelines for the State Disaster Relief Funds and National Disaster Relief Funds for 2026–31, with a combined corpus of INR 2 trillion for the State Disaster Response Fund and State Disaster Mitigation Fund (MHA 2026b, 2026a).
The HAP drafting process has evolved over time. The new generation of HAPs incorporate heat vulnerability and risk assessments to support ward-level planning, as seen in Jodhpur and Churu (Rajasthan), Thane (Maharashtra), Varanasi (Uttar Pradesh), and Mehsana (Gujarat); establish steering committees and pre-season stocktaking; and identify financing pathways through convergence with centrally sponsored schemes, municipal budgets, and corporate social responsibility funds (Kapoor et al. 2026). As of 2026, 23 states, 195 districts, and 64 cities have formalised their HAPs (NDMA 2026).
Certain aspects of preparedness and response are institutionalised. The NDMA oversees seasonal state-level preparedness, and coordinates with the India Meteorological Department for heatwave forecasts and early warning dissemination, and the Ministry of Health and Family Welfare (MoHFW) for reported health impacts across the country. Annual NDMA workshops provide platforms for knowledge exchange, and to showcase best practices from national and state governments, academic institutions, international experts, think tanks, implementation and development partners, and community members (NDMA 2024).
Strengthening heat-health preparedness and response
Historically, health sector responses to natural disasters have largely focused on disease-specific preparedness and local post-disaster response. However, the recognition of climate change’s widespread health impacts catalyzed streamlining of the heat-health response under the Health Mission of the Prime Minister’s Climate Council (PMCC) in 2014. In 2019, India’s health ministry began establishing a governance structure under the National Programme on Climate Change and Human Health (NPCCHH) to address extreme heat, among other climate-sensitive health issues (A. Kumar et al. 2020). The programme carries out the core mandate of climate changehealth adaptation and health system resilience through five key objectives: community awareness, health workforce capacity building, health facility and sectoral preparedness, multisectoral engagement through health-led task forces, and steering research.
By 2024, the NPCCHH had established nodal officers in all state, UT, and district health departments, and launched State Action Plans on Climate Change and Human Health (SAPCCHHs) including heat-health action plans (HHAPs) (Patel, Joshi, and Shrivastava 2026). They are funded centrally by the National Health Mission, MoHFW, in line with predetermined central-state shares. From 2020 to 2025, the budget allocated under the NPCCHH for states/UTs under the NHM was INR 2.49 billion (Ministry of Environment 2025). The district-level responses are now being formalised.
The heat-health response was further strengthened with the implementation of the National Action Plan on Heat Related Illnesses (2021), which includes clinical management, surveillance, and health facility preparedness protocols. It expanded with the digitisation of heat-health surveillance in 2023, extensive healthcare workforce capacity building efforts, and the integration of rapid, active cooling in clinical management in the form of heatstroke management units (HMU) and ambulance preparedness in 2024 (Patel, Joshi, and Shrivastava 2026). (Case Study 1)
The NHRIDS was upgraded to digital, daily, yeararound nationwide data collection in 2023 and casebased reporting in 2025, from paper-based, weekly, seasonal, heat-prone-state-focused reporting in 2015. Direct reporting from health facilities on the Integrated Health Information Platform with digital dashboards improved data quality, timeliness, representativeness, and utilisation. As of 2026, more than 50 per cent of about 51,000 health facilities nationwide, largely government-run, are reporting in NHRIDS (MHA 2026). Besides surveillance, field epidemiological investigations of heat-related mortality clustering provided critical understanding about the interplay of risk factors. In 2023, one such field investigation led to the inclusion of heat-focused public health and administrative guidance for mass gatherings and election-related planning, especially during summertime (N. Krishnan et al. 2025).
Guidelines, tools, advisories and training have increasingly evolved to meet the realities of intense and expanding seasonal heat, address diagnostic challenges, and incorporate new knowledge targeting all levels of healthcare professionals, health administrators, frontline workers, and the community (NPCCHH 2024b, 2024a, 2026). By 2024, all state, UT, and district nodal officers, as well as more than 18,600 medical officers, had been trained. Frontline workers have contributed to routine community-level health promotion activities and mass awareness campaigns (NPCCHH et al. 2024) (Case study 2)
Integration of heat exposure and related clinical and public health measures into other existing health programmes responding to communicable and non-communicable diseases is a developing agenda for the NPCCHH and MoHFW. The recent launch of guidelines and awareness content on heat and pregnancy is a step towards the vertical integration of heat into the existing, large national health programmes (NPCCHH 2026; Maternal Health Division, MoHFW 2026).
Emerging evidence links extreme heat to increased morbidity and mortality in India through direct and indirect impacts, in line with global evidence. Peer-reviewed research documents heat-related illnesses, increased cardiovascular and kidney disease risks, and adverse pregnancy outcomes, with higher risk among vulnerable populations. Urban heat islands, the built environment, physiological and medical vulnerabilities, and socioeconomic inequalities can further amplify health risks. A growing body of evidence also records occupational exposure and livelihood impacts, especially when heat exposure is associated with high workloads among outdoor and industrial workers. The resulting excess mortality, linked to rising temperatures, includes not only heatstroke deaths but also heat-contributed deaths. Evidence on the impact of extreme heat on other health domains is yet to emerge.
India is expanding Heat Action Plans across states, districts, and cities. The health sector is strengthening heat-health surveillance, enabling healthcare professionals and administrators, implementing heat-health action plans including initiatives like heatstroke management units and increasing community awareness and ambulance preparedness. Early warning and forecasting capabilities are enhanced for timely and wider dissemination. In 2026, heatwaves were declared a nationally notified natural disaster, which enables states to utilise national and state disaster mitigation funds for heat action. Responses from other government departments are nascent and sporadic. Apart from these, an extensive ecosystem of research, policy development and implementation support is simultaneously driven by non-governmental actors.
The report calls for institutionalising heat resilience across systems and sectors, moving beyond short-term response. This means mainstreaming heat action through joint planning, shared data and clear accountability, and strengthening institutional capacity, coordination and leadership. It also means making heat action health-centric, with health-based early warnings, stronger surveillance and clinical capacity, and access to water, shade, rest and cooling in workplaces and public spaces. Sustaining these efforts will require shifting from ad hoc funding to blended financing from public, private and climate sources.
India has made a promising start in strengthening heat action through the proliferation of heat action plans and expanded health surveillance; the next frontier is to institutionalise these plans and to assess whether the actions protect population health as intended. To achieve lasting change, we must place health outcomes at the centre of implementing and evaluating heat-health adaptation, while recognising that short-term responses need to be paired with systemic reforms and appropriate financing to build long-term resilience, alongside deep, continued climate mitigation in an increasingly warm world.


Living with Heat in Bangladesh



Unlocking Finance for Nature-based Solutions (NbS) in Indian Cities